

Why Understanding Pain Is Your First Step to Real Relief
To define pain is to understand a complex experience that is both physical and emotional. It’s more than a simple warning signal; it’s a personal journey that can persist long after an injury heals, affecting every part of your life.
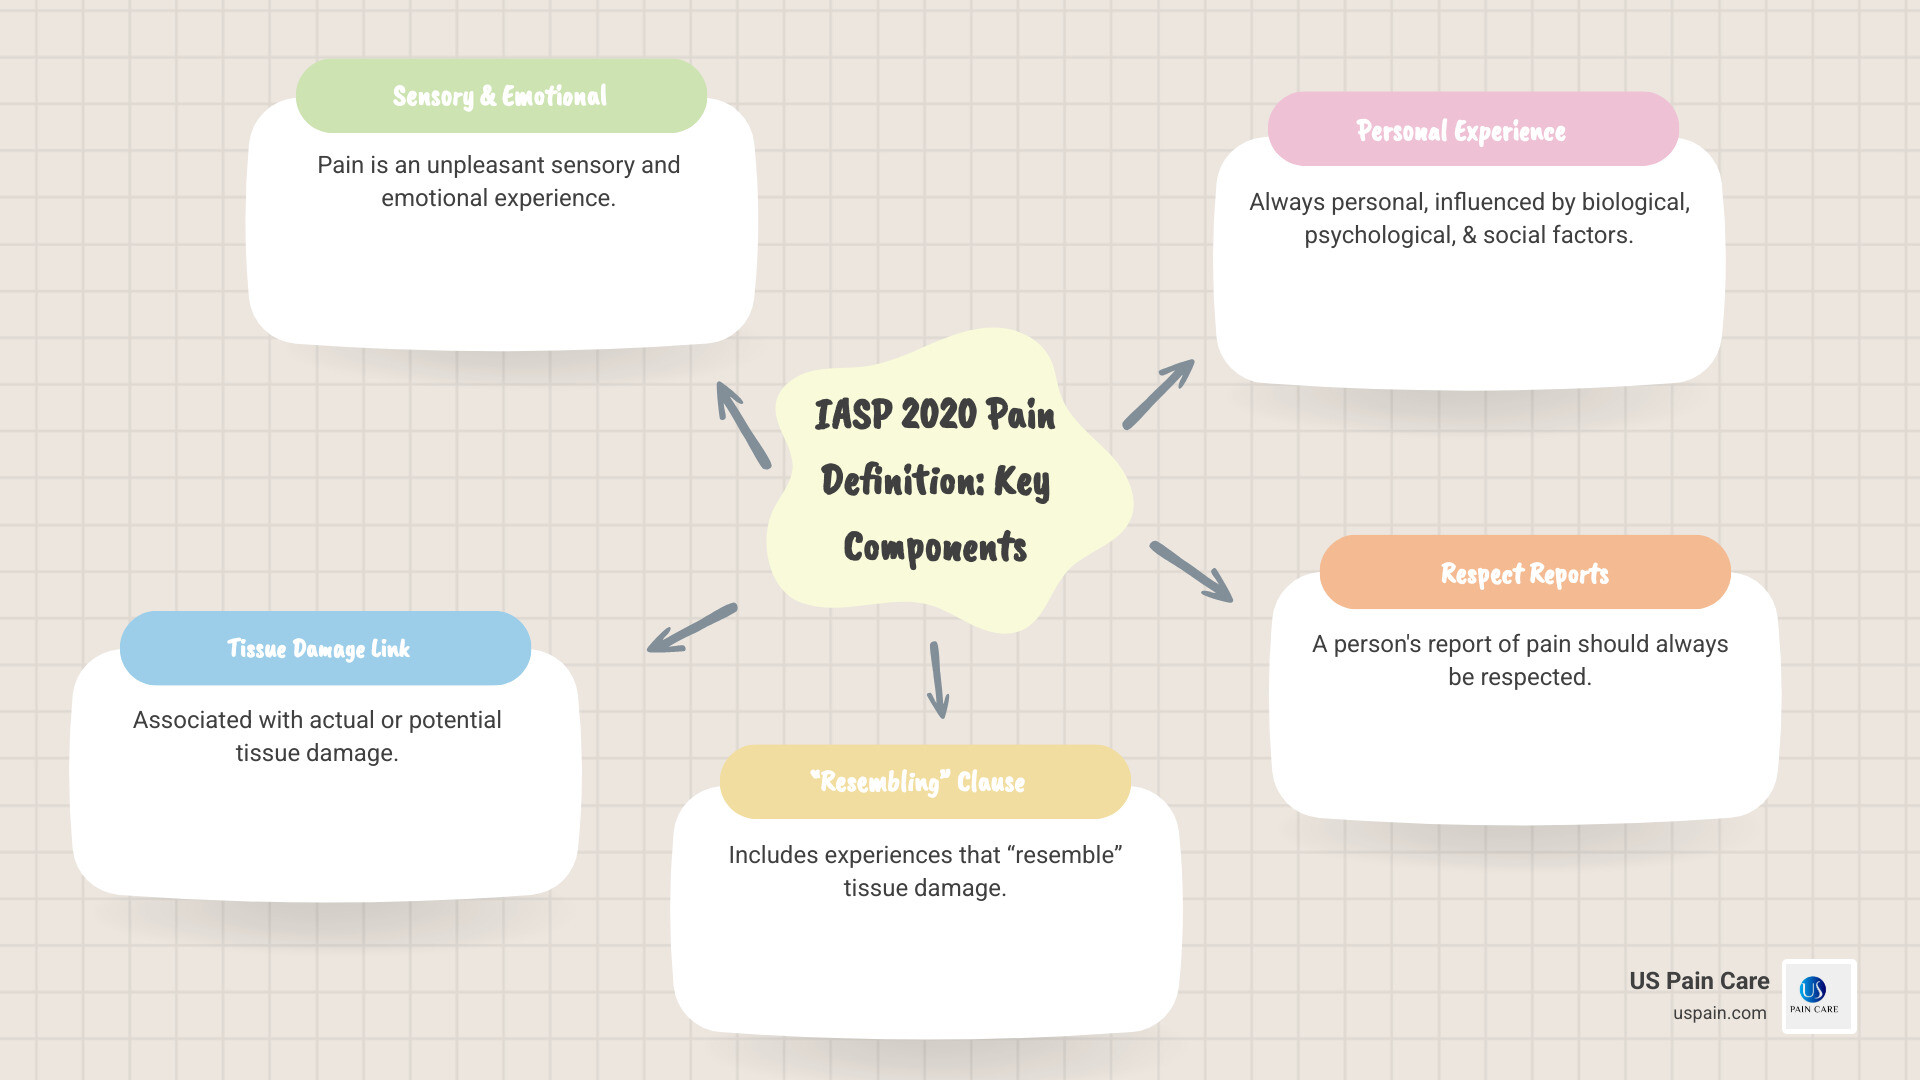
For decades, medicine used an outdated definition focused on tissue damage. In 2020, the International Association for the Study of Pain (IASP) introduced a landmark revision, finally acknowledging that pain is real, even when doctors can’t see it on a scan. This new definition recognizes pain as:
- “An unpleasant sensory and emotional experience”
- Associated with actual, potential, or even just “resembling” tissue damage
- A personal experience influenced by biological, psychological, and social factors
- Something that should be respected when reported by a patient
This guide will help you understand what pain truly is and how this knowledge can be your first step toward real relief.
I’m Dr. Paul Lynch, and with 17 years of experience treating complex pain conditions, I’ve seen that a clear understanding of pain is essential for managing it. When we define pain accurately, we can address its physical and emotional layers with the comprehensive care every patient deserves.
Basic define pain glossary:
The Official Definition of Pain: A Landmark Revision
For over 40 years, the medical world used a definition of pain that didn’t fully capture the patient experience. As our understanding grew, it became clear a change was needed.
In 2020, after years of research and input from experts and patients, the International Association for the Study of Pain (IASP) released a groundbreaking revision. This wasn’t a minor tweak; it was a reimagining of how we define pain, quickly adopted by the World Health Organization and healthcare professionals worldwide. You can read more about this process in The revised International Association for the Study of Pain definition: concepts, challenges, and compromises.
What is the IASP’s 2020 Definition?
Here is the definition that’s changing pain care:
“An unpleasant sensory and emotional experience associated with, or resembling that associated with, actual or potential tissue damage.”
Let’s break down why each part matters:
- “An unpleasant sensory and emotional experience” confirms that pain involves your whole self—your body, emotions, and mental state.
- “Associated with, or resembling that” is revolutionary. The word “resembling” validates pain even when an X-ray or MRI shows nothing wrong. It acknowledges the real pain of conditions like fibromyalgia or chronic back pain.
- “Actual or potential tissue damage” covers everything from a fresh injury to your body’s protective responses against possible harm.
How the Definition Evolved Over 40 Years
The previous 1979 definition was criticized for focusing too much on physical damage and failing to account for the mind-body connection.
In 2018, an IASP task force began the revision process. Crucially, they opened it to public consultation, receiving over 800 responses from 46 countries. Nearly half of these came from patients and caregivers. This feedback was vital, revealing that while many experts were satisfied with early drafts, a large number of patients were not. The final definition reflects a balance between scientific accuracy and the real-world experiences of people living with pain.
The Etymology of ‘Pain’: A Look Back
The word “pain” entered English in the 14th century from the Latin “poena,” meaning penalty or punishment. This origin reflects a historical view of pain as a consequence or moral judgment. While modern medicine sees pain as a complex biological and psychological process, these linguistic roots help explain why some people still feel shame or guilt about their pain. You can explore more at the Online Etymology Dictionary.
Decoding the Definition: The Six Key Notes Explained
The IASP’s definition includes six essential notes that provide a roadmap to understanding pain’s complexity. They transform a clinical definition into practical wisdom, helping us define pain beyond a simple “something hurts” approach.
Note 1: Pain is Always a Personal Experience
“Pain is always a personal experience that is influenced to varying degrees by biological, psychological, and social factors.”
Your pain is uniquely yours. Two people with the same injury can have vastly different pain levels due to:
- Biological factors: Genetics, hormones, and how your nervous system is wired.
- Psychological factors: Emotions, beliefs about pain, and past trauma.
- Social factors: Cultural background, family attitudes, and your support system.
Note 2: Differentiating Pain and Nociception
“Pain and nociception are different phenomena. Pain cannot be inferred solely from activity in sensory neurons.”
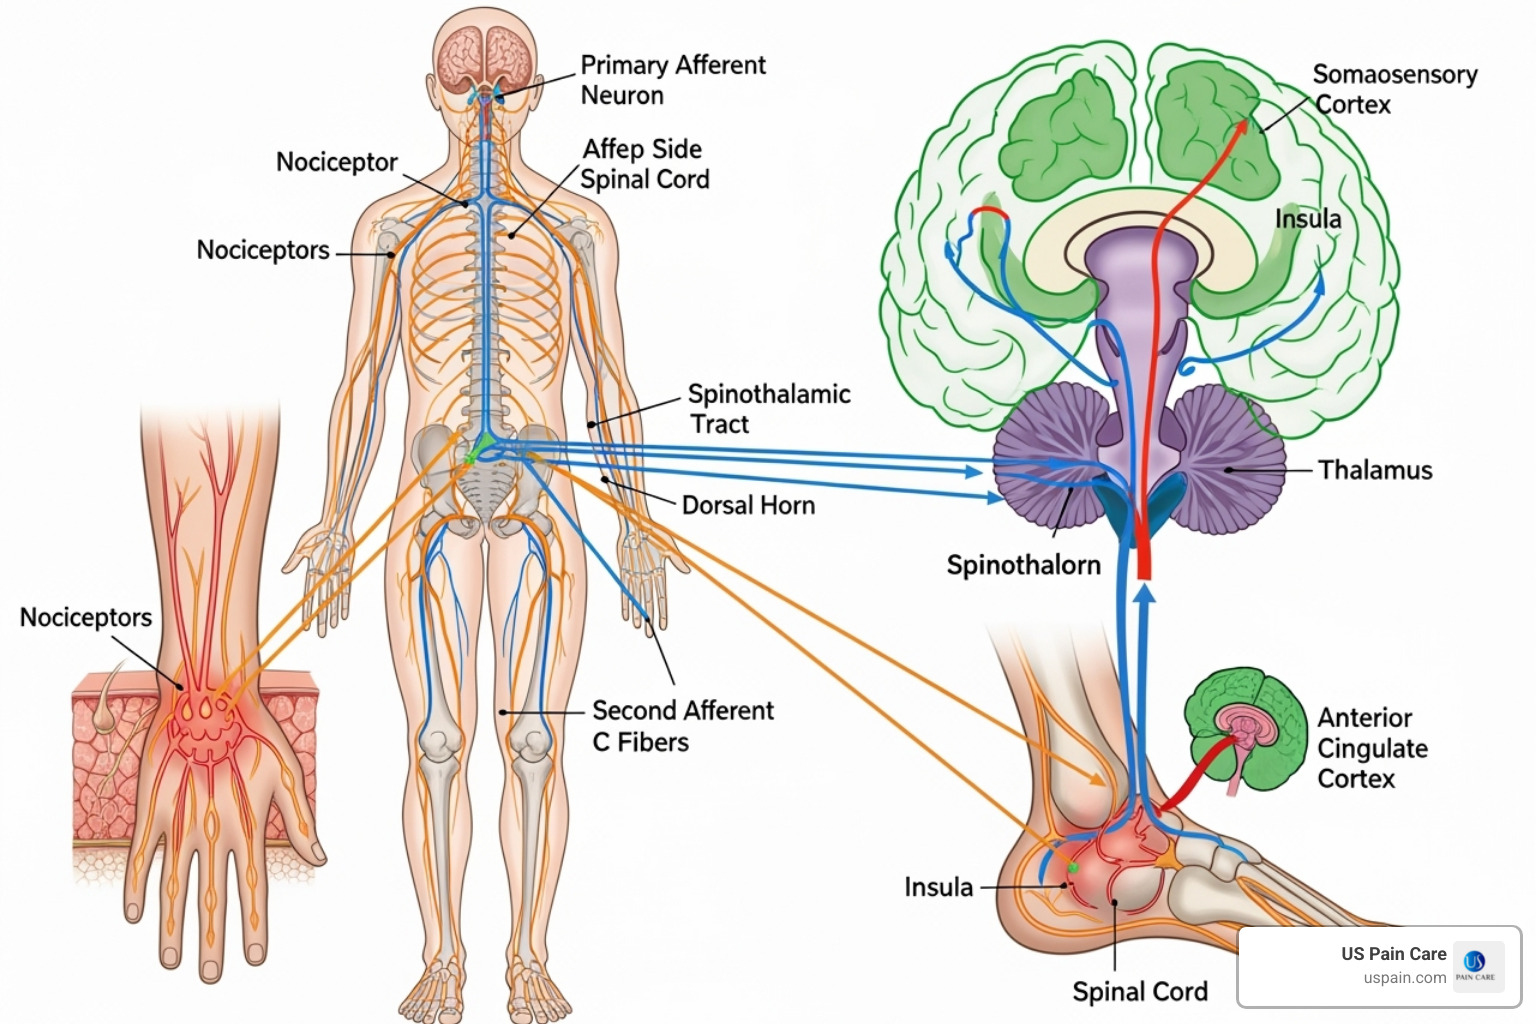
Nociception is the neural process of detecting potential harm—the alarm signal. Pain is the brain’s interpretation and emotional response to that signal. Think of nociception as the smoke detector, while pain is your brain deciding if there’s a real fire. This explains phantom limb pain (pain without nociception) and why athletes may not feel an injury until after a game (nociception without pain).
Note 3: Learning Through Life Experiences
“Through their life experiences, individuals learn the concept of pain.”
From your first scraped knee, your brain builds a database of what pain means. Past experiences—good and bad—shape how you interpret new pain signals. A person whose childhood pain was dismissed may develop different responses than someone who received comfort and care.
Note 4: A Person’s Report of Pain Should Be Respected
“A person’s report of an experience as pain should be respected.”
This note is a powerful shift away from the “it’s all in your head” mentality. Since pain is subjective, your self-report is the gold standard for assessment. You are the expert on your own pain. Believing patients is the foundation of effective pain care, building trust and opening the door to real solutions.
Note 5: Pain’s Adaptive Role and Its Downsides
“Although pain usually serves an adaptive role, it may have adverse effects on function and social and psychological well-being.”
Pain evolved as a protective mechanism to promote survival. However, when pain persists beyond its useful warning period, it becomes maladaptive. Chronic pain is no longer a helpful signal but a disease state in itself, negatively impacting sleep, work, relationships, and mental health.
Note 6: How We Define Pain in Non-Verbal Individuals
“Verbal description is only one of several behaviors to express pain; inability to communicate does not negate the possibility that a human or a nonhuman animal experiences pain.”
This note extends compassion to those who cannot speak, such as infants, individuals with cognitive impairments, and animals. Healthcare providers learn to observe behaviors like facial expressions, body posturing, or changes in activity to assess pain. It’s an ethical reminder that pain is a universal experience.
The Many Faces of Pain: Types and Classifications
To define pain effectively, we must recognize its different forms. Classifying pain helps healthcare providers choose the right treatment, much like using the right key for a specific lock.
Acute vs. Chronic Pain
The most basic classification is by duration.
Acute pain is your body’s normal alarm system. It’s sharp, immediate, and serves a purpose, warning you of injury. It typically resolves within days or weeks as the body heals. Acute pain management focuses on comfort during the healing process.
Chronic pain is different. It’s pain that lasts longer than three months, persisting after an initial injury should have healed. It stops being a symptom and becomes a condition in itself, affecting sleep, mood, and daily function. The IASP classification of chronic pain for ICD-11 treats it as a distinct medical disease.
Mechanistic Types of Pain
Understanding the underlying mechanism of pain is key to treatment.
Nociceptive pain is a direct response to tissue damage, like a cut, a broken bone, or arthritis. The pain signals originate from specialized nerve endings (nociceptors). This type often responds well to traditional pain medications like anti-inflammatories.
Neuropathic pain results from damage or dysfunction of the nervous system itself. Nerves send false alarm signals, causing sensations often described as burning, shooting, tingling, or electric shocks. Conditions like diabetic neuropathy, shingles, and sciatica cause this type of pain. Neuropathic pain treatment options often require specialized medications.
Nociplastic pain is a newer category describing pain from an altered pain processing system. The nervous system becomes hypersensitive, amplifying sensations. There is no clear tissue or nerve damage, but the brain and spinal cord have changed how they interpret signals. Conditions like fibromyalgia and some forms of chronic low back pain involve nociplastic mechanisms.
Understanding these types is why US Pain Care customizes treatments. Explore our chronic pain conditions library to learn more.
Beyond the Definition: The Biopsychosocial Experience of Pain
To truly define pain, we use the biopsychosocial model. This approach recognizes that pain is a complex experience created by the interplay of your body, mind, and social environment. It explains why two people with the same injury on an MRI can have vastly different pain levels.

The Biological Component
This is the physical foundation of your pain experience.
- Genetics: Your DNA can influence your pain tolerance and how you produce natural painkillers.
- Inflammation: While protective initially, chronic inflammation can keep pain signals firing.
- Neurochemistry: Brain chemicals (neurotransmitters) can either amplify or dampen pain signals.
- Nervous System Sensitization: Your pain system can become hypersensitive over time, turning up the “volume” on pain.
The Psychological Component
Your mind has incredible power over how you experience pain.
- Emotions: Anxiety, depression, and anger can physically amplify pain signals.
- Beliefs: Believing pain equals permanent damage can increase suffering. Understanding that pain doesn’t always mean harm can be liberating.
- Coping Strategies: Techniques like mindfulness and pacing can make pain more manageable, while fear-avoidance can make it worse.
- Stress and Trauma: Chronic stress and past trauma can rewire your nervous system to be more reactive to pain.
The Social Component
Your social world profoundly shapes your pain.
- Cultural Background: This influences how you express pain and what treatments you consider acceptable.
- Social Support: A strong support system can be as powerful as medication, while isolation can make pain feel unbearable.
- Work and Economic Factors: Financial stress and unaccommodating jobs can perpetuate a pain cycle.
- Social Stigma: Facing skepticism from others adds a layer of psychological suffering to physical pain.
Understanding these interconnected factors is why effective pain treatment requires a team approach that addresses the whole person.
How the Definition Impacts Assessment and Management
When we define pain using the IASP’s comprehensive framework, it changes how we approach pain care. This has practical implications for assessment, treatment, and the overall patient experience.
The Challenge of Assessing a Subjective Experience
Assessing pain means trying to measure something invisible and personal.
- Pain scales (like the 0-10 scale) are useful for tracking intensity but miss the full picture of how pain affects a person’s life.
- Self-reporting is the gold standard, but it can be limited by a patient’s desire to seem strong, difficulty finding words, or cultural background.
- For non-verbal individuals, providers must act as detectives, observing behavioral clues like grimacing or posturing.
- Unconscious bias can lead providers to underestimate pain, particularly in women and minority groups—a problem the new definition directly challenges.
- An objective “pain meter” remains elusive. Brain imaging shows activity, but it can’t capture the subjective human experience.
Why a Clear Definition Matters for Treatment
A comprehensive definition leads to better treatment strategies.
- Targeted Choices: Understanding the pain type (nociceptive, neuropathic, nociplastic) allows for more targeted therapies.
- Patient Validation: The definition’s “resembling” clause helps providers validate a patient’s pain, even without clear findings on a scan. This shift from doubt to belief is transformative.
- Multidisciplinary Care: The biopsychosocial model naturally leads to team-based care involving physicians, physical therapists, and psychologists, like the multimodal pain management approach at US Pain Care.
- Stigma Reduction: Officially recognizing that severe pain can exist without visible damage helps combat the stigma that chronic pain is a sign of weakness.
Impact on Research and Patient Care
The new definition is reshaping healthcare systems and research.
- Research Standardization: A universal definition allows scientists worldwide to compare studies and build knowledge faster.
- New Research Directions: The broader definition has opened up new avenues of study into central sensitization, social factors, and psychological interventions.
- Major Funding: Initiatives like the NIH HEAL Initiative are investing heavily in understanding pain’s complexity and finding non-opioid solutions.
- Patient-Provider Relationships: When providers listen, validate, and recognize pain’s complexity, trust is built, leading to more accurate assessments and effective treatment plans.
Frequently Asked Questions about Defining Pain
When I explain how we define pain to my patients, a few key questions often arise. Answering them helps clear up common misconceptions that can be barriers to effective care.
Can you have pain without any physical injury?
Yes, absolutely. The IASP definition’s “resembling” clause was included specifically for this reason. Your pain is real even when scans are normal.
This occurs in conditions involving nociplastic pain (like fibromyalgia), where the nervous system’s processing of signals is altered, or neuropathic pain (like phantom limb pain), where the pain is generated by the nerves themselves, not an external injury. Pain is a complex output from the brain, not just a simple response to tissue damage.
Is emotional pain considered “real” pain?
Yes. The definition explicitly calls pain a “sensory and emotional experience.” The emotional part isn’t separate; it’s integral to what pain is.
Neuroscience shows that the brain regions activated by physical injury also light up during experiences of social rejection or grief. This is why emotional distress can cause very real physical sensations of pain. The mind and body are a single, interconnected system.
Why did the IASP change the definition of pain after 40 years?
The definition was revised because our scientific understanding of pain evolved dramatically. The change was necessary for several reasons:
- Scientific Advances: We finded concepts like central sensitization and nociplastic pain, which the old definition didn’t cover.
- Patient Voices: People with chronic pain felt the old definition, with its focus on tissue damage, invalidated their experience.
- Inclusivity: The new definition and its notes better account for pain in non-verbal individuals, like infants or people with dementia.
- Clinical Necessity: Doctors needed a framework that helps them treat the full spectrum of pain conditions, not just those with obvious physical causes.
Conclusion
To define pain is to recognize it as a complex, personal, and biopsychosocial experience. The IASP’s 2020 revision has revolutionized our approach, validating that pain is real even when it’s not visible on a scan. This comprehensive understanding—that pain is an “unpleasant sensory and emotional experience associated with, or resembling that associated with, actual or potential tissue damage”—opens the door to more compassionate and effective care.
Understanding what pain is forms the foundation for relief. It moves us beyond outdated thinking and toward a whole-person approach that considers the biological, psychological, and social factors of your unique pain journey. The six key notes accompanying the definition provide a roadmap, emphasizing that your report of pain must be respected.
At US Pain Care, our patient-first philosophy aligns with this modern understanding. We provide advanced, integrated treatments that address the whole person, offering cutting-edge, minimally invasive options for those who haven’t found relief elsewhere.
If you’re struggling with pain and feel misunderstood, know that this new definition validates your experience. Your pain is real, and it deserves comprehensive care. To explore a different approach to pain management, we invite you to explore our advanced chronic pain management services. Our team is here to help you reclaim your life.