
Table of Contents
Pelvic Pain
This article was medically reviewed and approved by Dr. Zach Cohen.
Pelvic pain is a common condition that affects both men and women but is more prevalent in women due to reproductive anatomy. It refers to pain occurring in the lowest part of the abdomen and pelvis. The sensation can range from mild and intermittent discomfort to severe and chronic pain that significantly impacts daily activities.
Pelvic pain may arise from various causes, including issues related to the reproductive, urinary, digestive, or musculoskeletal systems. It can be acute, lasting a few hours or days, or chronic, persisting for six months or longer. Understanding the underlying causes and addressing them is vital for effective treatment and improving quality of life.
Symptoms/Causes
Symptoms
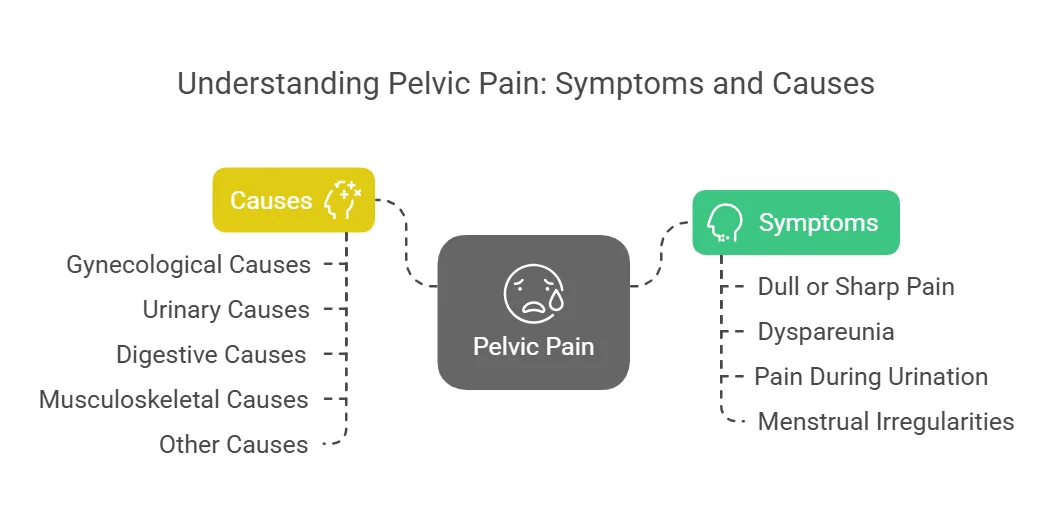
Pelvic pain can manifest in different ways depending on the underlying cause. Common symptoms include: MedlinePlus explains that pelvic pain mostly occurs in the lower abdomen and may be steady or come and go, sharp or dull.
- Dull, aching, or sharp pain localized in the pelvic region.
- Pain during sexual intercourse (dyspareunia).
- Pain during urination or bowel movements.
- Menstrual irregularities and cramping.
- Pressure or heaviness in the pelvic area.
- Pain radiating to the lower back or thighs.
- Discomfort aggravated by prolonged sitting or standing.
Causes
Pelvic pain stems from various sources, including:
- Gynecological Causes:
- Endometriosis
- Ovarian cysts
- Pelvic inflammatory disease (PID)
- Uterine fibroids
- Ectopic pregnancy
- Menstrual disorders
- Urinary Causes:
- Urinary tract infections (UTIs)
- Interstitial cystitis (painful bladder syndrome)
- Kidney stones
- Digestive Causes:
- Irritable bowel syndrome (IBS)
- Inflammatory bowel disease (IBD)
- Constipation or bowel obstruction
- Musculoskeletal Causes:
- Pelvic floor muscle dysfunction
- Hernias
- Chronic lower back pain
- Other Causes:
- Psychological factors such as stress and depression
- Nerve-related pain (neuropathy)
Diagnosis/Tests
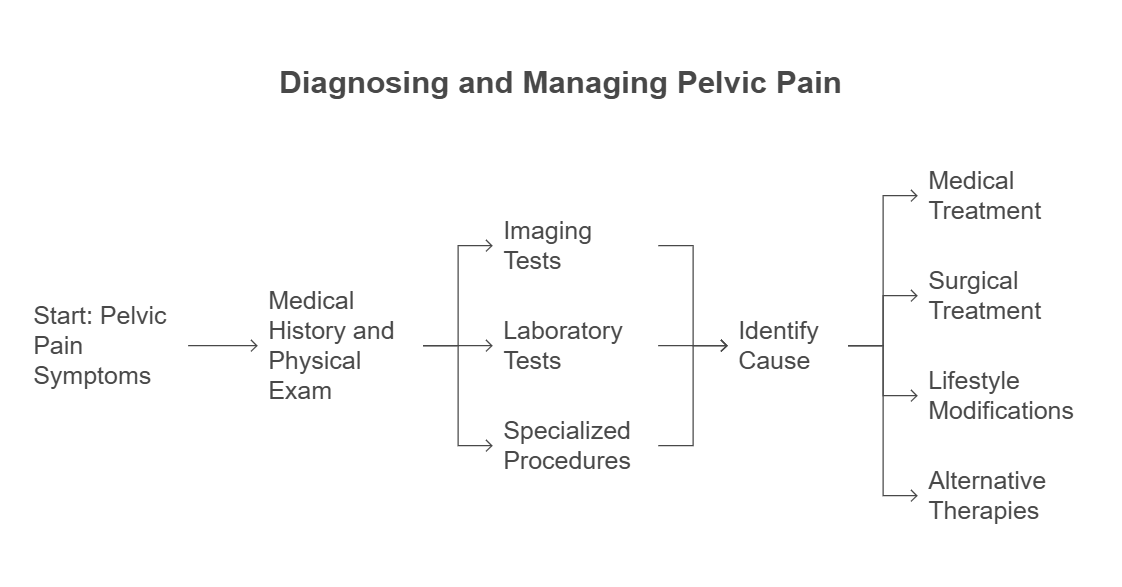
Diagnosing pelvic pain involves a detailed medical history, physical examination, and diagnostic tests to identify the root cause. These include: Finding the cause may require lab tests, imaging, or other tests such as a pelvic exam, laparoscopy, or pelvic ultrasound, according to MedlinePlus.
- Medical History and Physical Exam:
- Discussion of symptoms, onset, and severity.
- Examination of the pelvic area, abdomen, and lower back.
- Imaging Tests:
- Ultrasound to visualize reproductive organs.
- CT scan or MRI for detailed imaging of pelvic structures.
- Laboratory Tests:
- Blood tests to detect infections or inflammation.
- Urinalysis for urinary infections.
- Specialized Procedures:
- Laparoscopy to examine internal organs and diagnose conditions like endometriosis.
- Colonoscopy to assess bowel-related issues.
- Cystoscopy to evaluate the bladder and urethra.
- Pain Mapping:
- Identification of pain triggers through physical palpation or imaging guidance.
Management/Treatment
The treatment of pelvic pain depends on the identified cause and may involve a combination of medical, surgical, and lifestyle interventions.
Medical Treatment
- Medications:
- Pain relievers (NSAIDs, acetaminophen).
- Hormonal therapies for gynecological conditions.
- Antibiotics for infections.
- Neuropathic pain medications (e.g., gabapentin).
- Physical Therapy:
- Pelvic floor therapy to strengthen and relax muscles.
- Exercises to improve posture and mobility.
Surgical Treatment
- Laparoscopic surgery for endometriosis or fibroids.
- Hysterectomy in severe gynecological cases.
- Surgical repair of hernias or bowel obstructions.
Lifestyle Modifications
- Stress management techniques such as yoga and meditation.
- Dietary changes to alleviate IBS or urinary symptoms.
- Regular exercise to improve overall pelvic health.
Alternative Therapies
- Acupuncture for pain relief.
- Cognitive behavioral therapy (CBT) for managing chronic pain.
Treatment of Superior and Inferior Hypogastric Plexus Blocks for Pelvic Pain
Pelvic pain is a complex and often debilitating condition that can significantly impact a person’s quality of life. It can result from various underlying causes, including endometriosis, interstitial cystitis, chronic prostatitis, and pelvic organ diseases. Treatment options for chronic pelvic pain (CPP) are often multidisciplinary, involving medications, physical therapy, and surgical interventions. However, when conservative treatments fail, nerve blocks such as superior and inferior hypogastric plexus (SHP and IHP) blocks have gained attention as an effective means of managing pelvic pain, particularly when pain is centralized in the pelvic region.
Mechanism of Action for Pain Relief
The superior and inferior hypogastric plexuses are major nerve centers that innervate the pelvic organs, including the uterus, bladder, and rectum. The SHP is located in the abdomen near the aorta, while the IHP is found within the pelvis near the sacral promontory. These plexuses are responsible for transmitting pain signals from the pelvic organs to the brain.
When a block is performed, local anesthetics or neurolytic agents are injected into or around these plexuses, interrupting the transmission of pain signals. The anesthetic temporarily prevents the nerves from relaying sensations of pain, providing relief. Neurolysis, which involves injecting an agent that damages the nerve fibers, can provide longer-lasting relief by permanently inhibiting pain transmission.
Medical Necessity – Indications for Procedure
SHP and IHP blocks are indicated for patients suffering from chronic pelvic pain, particularly when the pain is refractory to other treatments such as medication, physical therapy, and surgery. Some common indications for the procedure include:
- Endometriosis: Chronic pelvic pain due to endometriosis, particularly when it becomes resistant to other forms of treatment.
- Interstitial Cystitis: Chronic bladder pain and discomfort that does not respond to first-line treatments.
- Chronic Prostatitis: Long-standing pelvic pain in men often associated with prostatitis.
- Pelvic Organ Prolapse: Pain from conditions like uterine or bladder prolapse.
- Chronic Post-surgical Pain: Pain following pelvic surgeries that has become persistent.
This procedure is typically considered when conservative measures fail and the patient’s pain significantly impacts their quality of life.
Description of Procedure
The SHP and IHP block procedure is performed under fluoroscopic or CT guidance to ensure precise placement of the needle. The patient is positioned comfortably, often lying on their back, and the skin is sterilized.
- For the SHP block, a needle is inserted through the abdominal wall and advanced toward the area of the superior hypogastric plexus, just anterior to the aorta. Local anesthetic or neurolytic agent is injected to block nerve transmission.
- For the IHP block, the needle is inserted through the pelvic region, targeting the inferior hypogastric plexus, located near the sacral promontory. A similar injection is made to alleviate pain.
The entire procedure usually takes about 30 minutes, and patients are monitored for any immediate complications.
Post-op Instructions and Recovery
Post-procedure care is crucial for ensuring the best outcome and minimizing risks. Patients should follow these instructions:
- Rest and avoid strenuous activities for the first 24-48 hours to allow for healing.
- Hydration: Patients should drink plenty of fluids, as the anesthesia may cause temporary dryness in the mouth.
- Pain Management: Mild discomfort at the injection site may occur, which can usually be managed with over-the-counter pain relief.
- Follow-up Care: A follow-up appointment is typically scheduled within one week to assess the effectiveness of the block and address any complications.
Most patients can resume normal activities after 1-2 days, but full recovery and symptom relief may take up to 1-2 weeks. If neurolysis was performed, the effects may last longer, sometimes months or even years.
Prognosis
The prognosis following SHP and IHP blocks varies based on the patient’s underlying condition and the success of the procedure. Many patients experience significant pain relief, with some seeing improvements for several months or even years, particularly if neurolytic agents are used. For others, the benefits may be temporary, necessitating repeat procedures or adjunct treatments.
In general, these blocks can greatly enhance the quality of life for individuals with chronic pelvic pain by reducing reliance on medications and improving overall pelvic function. However, they may not be suitable for all patients, particularly those with certain underlying conditions like infections or malignancies in the pelvic region.
In summary, superior and inferior hypogastric plexus blocks are an effective intervention for managing chronic pelvic pain, with a solid body of research supporting their benefits. These procedures provide an option for patients who have not found relief through traditional treatments, improving quality of life and reducing the need for invasive surgeries.
**Radiofrequency Ablation (RFA) for Pelvic Pain
**
Pelvic pain, often chronic, is a complex and debilitating condition that affects both men and women. It can arise from various sources, including gynecological, urological, gastrointestinal, and musculoskeletal conditions. For many patients with chronic pelvic pain (CPP), conventional treatments such as medications, physical therapy, and surgery may provide limited relief. In recent years, radiofrequency ablation (RFA) has emerged as an effective treatment modality, particularly for individuals with refractory pelvic pain. RFA is a minimally invasive procedure that uses heat to target and disrupt nerve pathways responsible for transmitting pain signals.
Mechanism of Action for Pain Relief
RFA works by using heat to target specific nerves that transmit pain signals from the pelvic organs to the brain. The procedure involves the insertion of a needle-like electrode into the targeted area, where radiofrequency energy is applied to generate heat. This heat causes a lesion to form on the nerve, disrupting its ability to transmit pain signals. In some cases, the nerve may be permanently damaged, providing long-lasting pain relief. RFA is typically performed under imaging guidance, such as fluoroscopy or ultrasound, to ensure precise targeting of the nerve.
RFA is particularly effective for treating pain related to the following nerve structures:
- Pelvic Nerves: These nerves transmit pain signals from the uterus, bladder, and rectum.
- Hypogastric Plexus: A network of nerves responsible for transmitting sensations from the lower abdomen and pelvis.
- Pudendal Nerve: A major nerve that supplies sensation to the pelvic floor and genital areas.
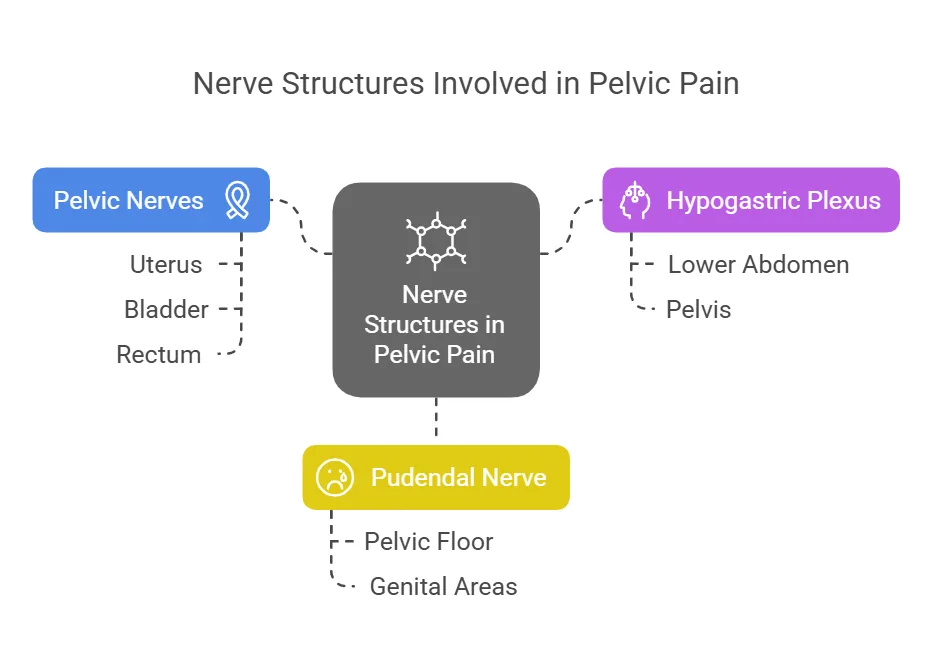
By targeting and disrupting these pathways, RFA can offer significant relief from chronic pelvic pain.
Medical Necessity – Indications for Procedure
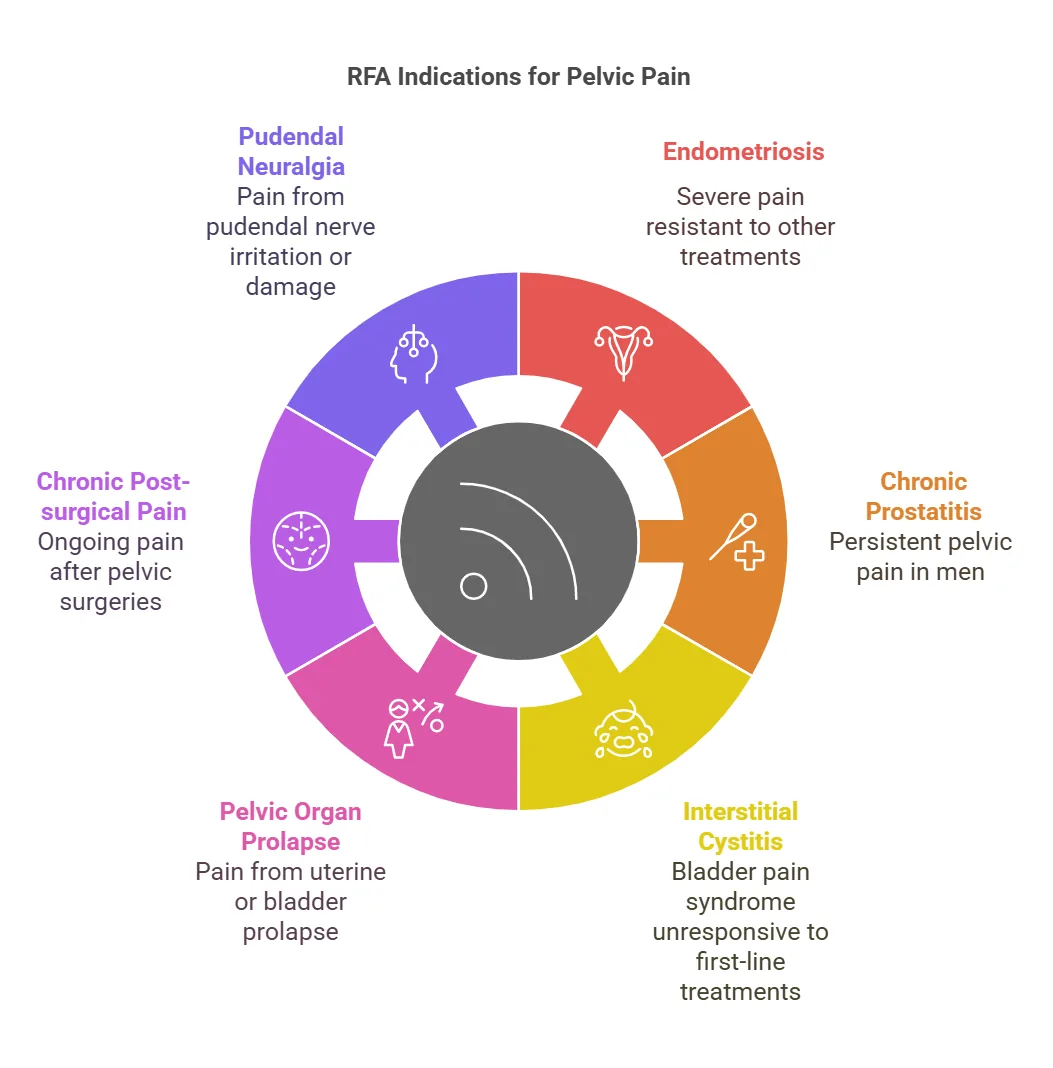
RFA is indicated for patients with chronic pelvic pain that is not responsive to conservative treatments like medications, physical therapy, or nerve blocks. Some specific conditions for which RFA may be indicated include:
- Endometriosis: When endometriosis-related pain is severe and resistant to other forms of treatment.
- Chronic Prostatitis: For men suffering from persistent pelvic pain due to prostatitis.
- Interstitial Cystitis: For patients with bladder pain syndrome that has not responded to first-line treatments.
- Pelvic Organ Prolapse: Pain from conditions such as uterine or bladder prolapse.
- Chronic Post-surgical Pain: Persistent pain following pelvic surgeries, such as hysterectomy or prostatectomy.
- Pudendal Neuralgia: Pain caused by irritation or damage to the pudendal nerve.
The procedure is considered when pain significantly affects a patient’s quality of life and other treatments have been ineffective or are not viable.
Description of Procedure
RFA is a minimally invasive procedure performed under local anesthesia and imaging guidance, such as fluoroscopy or ultrasound, to ensure precision. The procedure generally follows these steps:
- Preparation: The patient is positioned comfortably, typically lying on their back. Local anesthesia is administered to numb the area where the needle will be inserted.
- Needle Insertion: A thin, needle-like electrode is inserted through the skin, guided by imaging to the target nerve or nerve bundle.
- Radiofrequency Energy Application: Once the needle is in position, radiofrequency energy is passed through the electrode to heat the targeted nerve. This heat disrupts the nerve’s ability to transmit pain signals.
- Post-procedure Care: The needle is removed, and the patient is monitored for any immediate complications.
The procedure typically lasts between 30-60 minutes, depending on the complexity of the case. It is usually done on an outpatient basis, meaning patients can go home the same day.
Post-op Instructions and Recovery
Following the RFA procedure, patients may experience mild discomfort at the injection site, but this generally resolves within a few days. Key post-procedure instructions include:
- Rest: Patients are advised to rest for 24-48 hours and avoid strenuous activities.
- Pain Management: Over-the-counter pain relievers, such as acetaminophen or ibuprofen, can help manage any post-procedural discomfort.
- Monitor for Side Effects: Patients should watch for signs of infection at the injection site or unusual pain. If these occur, medical attention should be sought.
- Follow-up Appointments: A follow-up visit is typically scheduled within one to two weeks to assess the effectiveness of the procedure and monitor recovery.
Most patients are able to return to normal activities within a few days, though complete pain relief may take several days or weeks to manifest. For some patients, additional procedures may be necessary if pain relief is not sustained.
Prognosis
The prognosis for patients undergoing RFA for pelvic pain is generally positive, with many experiencing significant and lasting pain relief. Pain reduction can range from 50-80%, depending on the underlying cause and the precision of the procedure. For patients with conditions like endometriosis or interstitial cystitis, RFA can significantly reduce pain and improve quality of life, often with fewer side effects than traditional pain management methods such as narcotics.
However, the duration of pain relief can vary. Some patients may experience long-term relief, while others may require additional procedures after several months or years. The need for repeat procedures depends on the nature of the pain and the nerves treated.
In summary, radiofrequency ablation offers a promising and minimally invasive treatment for chronic pelvic pain, particularly in cases where other treatments have failed. With the potential for significant pain relief and improved quality of life, RFA is increasingly becoming a go-to option for patients dealing with persistent and debilitating pelvic pain.
Bilateral Sacral S2 or S3 Transforaminal Epidural Steroid Injections (TFESI) for Pelvic Pain
Pelvic pain is a common and multifaceted condition that can significantly disrupt a patient’s quality of life. It can arise from various etiologies, including musculoskeletal, urological, gynecological, and gastrointestinal disorders. Chronic pelvic pain (CPP) often persists despite conventional treatments such as medications, physical therapy, and nerve blocks. Among newer intervention strategies, bilateral sacral S2 or S3 transforaminal epidural steroid injections (TFESI) have gained attention for their potential to manage pain related to the lower back and pelvic region, especially in cases of pelvic organ dysfunction or nerve irritation. TFESI targets specific nerves that transmit pain signals from the pelvis, providing effective pain relief for many patients.
Mechanism of Action for Pain Relief
Transforaminal epidural steroid injections (TFESI) involve the delivery of corticosteroids directly to the epidural space near the affected nerves. The sacral nerves, including those at the S2 and S3 levels, innervate the pelvic organs and pelvic floor, transmitting pain signals from the bladder, uterus, rectum, and other pelvic structures to the brain.
The TFESI procedure targets the specific nerve roots at the S2 or S3 level, which are associated with the pelvic region. The corticosteroids injected into the epidural space reduce inflammation around these nerve roots and disrupt pain transmission. By alleviating the inflammation and irritation of these nerves, TFESI can provide significant pain relief, often within a few days of the procedure. The steroid medication also helps to diminish swelling and irritation, leading to a reduction in pelvic pain.
Medical Necessity – Indications for Procedure
Bilateral sacral S2 or S3 TFESI is indicated for patients suffering from chronic pelvic pain that is not adequately managed through conservative treatments such as medications or physical therapy. Specific indications for TFESI include:
- Chronic Pelvic Pain: Pain arising from pelvic organ dysfunction, including bladder, uterine, or rectal pain.
- Pelvic Organ Prolapse: Pain related to the displacement of pelvic organs that causes discomfort and pressure.
- Interstitial Cystitis: A chronic condition causing bladder pain, urgency, and frequency.
- Chronic Prostatitis: Pelvic pain due to prostatitis that does not respond to antibiotics or other treatments.
- Pudendal Neuralgia: Pain caused by irritation or compression of the pudendal nerve.
- Post-surgical Pain: Persistent pelvic pain following procedures such as hysterectomy, prostatectomy, or other pelvic surgeries.
- Pelvic Floor Dysfunction: Dysfunction of the pelvic floor muscles leading to chronic pain and discomfort.
The procedure is considered when the pelvic pain significantly affects a patient’s quality of life and other treatments have not provided adequate relief.
Description of Procedure
Bilateral sacral S2 or S3 TFESI is typically performed under fluoroscopic (X-ray) guidance to ensure precise placement of the needle and minimize the risk of complications. The procedure involves the following steps:
- Preparation: The patient is positioned comfortably, usually lying on their stomach. The area is sterilized, and local anesthesia is administered to numb the skin and tissues around the injection site.
- Needle Insertion: A thin needle is carefully inserted through the skin, guided by fluoroscopy, and advanced to the targeted area around the sacral nerve roots at the S2 or S3 levels.
- Injection: Once the needle is correctly positioned, a small amount of corticosteroid and anesthetic is injected into the epidural space, near the sacral nerve roots. This delivers the medication to reduce inflammation and block pain transmission.
- Post-injection Care: The needle is removed, and the patient is monitored for any immediate adverse reactions or complications.
The procedure typically takes between 15 to 30 minutes and is performed on an outpatient basis. Most patients can go home the same day after the procedure.
Post-op Instructions and Recovery
Following bilateral sacral S2 or S3 TFESI, patients may experience mild soreness at the injection site. Post-operative instructions include:
- Rest: Patients are advised to rest for the first 24-48 hours after the procedure to allow the medication to take effect.
- Pain Management: Mild discomfort or soreness can be managed with over-the-counter pain relievers such as acetaminophen or ibuprofen.
- Avoid Strenuous Activity: Patients should refrain from heavy lifting or strenuous exercise for at least one week following the injection to avoid irritation of the injection site.
- Hydration: Drinking plenty of fluids helps reduce the risk of complications such as headaches or dizziness.
- Follow-up: A follow-up visit is typically scheduled within one to two weeks to evaluate the effectiveness of the injection and determine if additional treatments are necessary.
Most patients can return to normal activities within a few days, although pain relief may take up to one week to become noticeable. The effects of the corticosteroids can last anywhere from several weeks to several months, depending on the individual.
Prognosis
The prognosis following bilateral sacral S2 or S3 TFESI is generally positive, with many patients experiencing significant pain relief and improved function. Studies suggest that 50-75% of patients report a reduction in pelvic pain by at least 50%, with some patients enjoying relief for several months following the procedure.
However, the duration of pain relief can vary. While some patients experience long-term benefits, others may require repeat injections after several months. TFESI is particularly effective for managing inflammation and nerve-related pain, but it may not be a permanent solution for all patients, especially those with progressive or worsening underlying conditions.
In summary, bilateral sacral S2 or S3 TFESI is an effective and minimally invasive option for managing chronic pelvic pain, especially in cases where conservative treatments have failed. With a strong track record of success, this procedure provides patients with significant relief, improved quality of life, and a reduction in the need for opioid medications or more invasive interventions.
Ilioinguinal, Iliohypogastric, and Genitofemoral Nerve Block for Pelvic Pain
Pelvic pain is a widespread condition that can significantly impact a patient’s quality of life. It can result from a variety of underlying causes, including gynecological, urological, musculoskeletal, and gastrointestinal disorders. When pelvic pain becomes chronic or resistant to traditional treatments, nerve blocks can offer a promising alternative. The ilioinguinal, iliohypogastric, and genitofemoral nerves are responsible for transmitting sensory information from the pelvic region to the brain. These nerves supply sensation to areas such as the lower abdomen, groin, and external genitalia. A nerve block targeting these nerves can effectively reduce pain by interrupting pain signals from these regions, making it a useful tool for managing chronic pelvic pain.
Mechanism of Action for Pain Relief
The ilioinguinal, iliohypogastric, and genitofemoral nerves are responsible for providing sensory innervation to the lower abdomen, groin, and external genitalia. Pain originating from pelvic organs such as the bladder, uterus, or prostate can be transmitted through these nerves to the brain.
- The Ilioinguinal and Iliohypogastric Nerves: These nerves arise from the lower lumbar spine (L1 and L2) and provide sensation to the lower abdomen, groin, and upper thigh. They also play a role in the sensation of pain related to pelvic organ dysfunction.
- The Genitofemoral Nerve: This nerve arises from the L1 and L2 spinal nerves and provides sensory innervation to the genital area, groin, and upper thigh.
When a nerve block is performed, local anesthetic or neurolytic agents are injected near these nerves, interrupting their ability to transmit pain signals. This block prevents pain from being relayed from the pelvic region to the brain, resulting in effective pain relief. The analgesic effect can be temporary or longer-lasting, depending on the type of medication used.
Medical Necessity – Indications for Procedure
The ilioinguinal, iliohypogastric, and genitofemoral nerve blocks are indicated for patients experiencing chronic pelvic pain that is not responsive to conservative treatments. Specific indications for these nerve blocks include:
- Post-Surgical Pain: Persistent pain following abdominal or pelvic surgeries, including cesarean section, hernia repair, or hysterectomy.
- Pelvic Organ Dysfunction: Pain associated with conditions like interstitial cystitis, endometriosis, or pelvic floor dysfunction.
- Chronic Groin Pain: Pain in the groin area that may be due to nerve compression or irritation.
- Genital or Inguinal Pain: Pain in the genital region or inguinal area that does not respond to other treatments.
- Pelvic Nerve Irritation: Irritation of nerves that supply the pelvic organs, leading to chronic pain or discomfort.
The procedure is considered when the pain significantly affects a patient’s quality of life and other interventions, such as medications, physical therapy, or nerve blocks, have failed to provide relief.
Description of Procedure
The ilioinguinal, iliohypogastric, and genitofemoral nerve block is a relatively simple and minimally invasive procedure, typically performed under fluoroscopic or ultrasound guidance to ensure precise needle placement. The procedure generally follows these steps:
- Preparation: The patient is positioned comfortably, often lying on their back. The area to be injected is sterilized, and local anesthesia is administered to numb the skin.
- Needle Insertion: A fine needle is inserted through the skin and advanced toward the targeted nerve regions, usually near the inguinal ligament or just above the pelvic rim. Imaging guidance helps ensure accuracy.
- Injection: Once the needle reaches the appropriate location, a small amount of local anesthetic (and occasionally corticosteroid) is injected around the ilioinguinal, iliohypogastric, or genitofemoral nerves.
- Post-injection Care: After the injection, the needle is removed, and the patient is monitored for any immediate side effects or complications.
The procedure typically lasts 15-30 minutes and is done on an outpatient basis. Most patients can go home the same day.
Post-op Instructions and Recovery
Following the nerve block, patients may experience temporary soreness at the injection site. Post-operative instructions include:
- Rest and Observation: Patients should rest for 24 hours following the procedure, as the anesthetic takes effect. They should also refrain from heavy lifting or strenuous activities.
- Pain Management: Mild discomfort or soreness at the injection site can be managed with over-the-counter pain relievers such as acetaminophen or ibuprofen.
- Hydration: Drinking plenty of fluids helps alleviate any potential side effects, such as dry mouth, caused by the anesthesia.
- Follow-up: A follow-up appointment is typically scheduled within one to two weeks to evaluate the effectiveness of the procedure and monitor recovery. If pain relief is achieved, additional injections may be scheduled as necessary.
Most patients can return to normal activities within a few days, but full pain relief may take up to a week to manifest. The effects of the nerve block can last from a few weeks to several months, depending on the medication used and the underlying condition.
Prognosis
The prognosis for patients receiving an ilioinguinal, iliohypogastric, or genitofemoral nerve block is generally positive, with most individuals experiencing significant pain relief. Studies suggest that 60-80% of patients report a reduction in pain of at least 50%, and many experience a lasting improvement in both pain levels and quality of life.
The duration of pain relief can vary depending on the underlying condition. For some, the effects may last for several months, while others may require repeat injections. In cases where the nerve block provides long-lasting relief, it can reduce the need for other pain management interventions, such as opioids or invasive surgeries.
In summary, ilioinguinal, iliohypogastric, and genitofemoral nerve blocks offer an effective, minimally invasive option for managing chronic pelvic pain, particularly when other treatments have been unsuccessful. By targeting specific nerves that transmit pain signals from the pelvic region, these blocks can provide significant relief and improve overall patient well-being.
Prevention
Preventing pelvic pain involves maintaining overall health and addressing risk factors:
- Regular Medical Check-ups:
- Early detection of conditions like infections or fibroids.
- Healthy Lifestyle:
- Balanced diet rich in fiber to prevent constipation.
- Adequate hydration to reduce UTIs and kidney stones.
- Regular physical activity to strengthen core and pelvic muscles.
- Safe Practices:
- Safe sexual practices to avoid STIs.
- Proper hygiene during menstruation.
- Stress Management:
- Reducing psychological stress through relaxation techniques.
Outlook/Prognosis
The prognosis for pelvic pain varies widely depending on the cause. Acute conditions like infections often resolve with prompt treatment, while chronic pelvic pain may require long-term management. Multidisciplinary approaches that address physical, emotional, and psychological factors typically yield the best outcomes.
Patients with chronic pelvic pain are encouraged to work closely with healthcare providers to identify and treat underlying issues, ensuring improved quality of life and minimized discomfort.
Frequently Asked Questions
What causes chronic pelvic pain?
Causes vary. MedlinePlus lists problems of the reproductive organs in women, the prostate in men, and infection or problems of the urinary tract, bowel, muscles, or bones in both. Some people have more than one cause at once, so careful evaluation matters.
When should I see a doctor for pelvic pain?
See a doctor if pelvic pain is severe, lasts more than a few weeks, interferes with daily activities, or comes with fever, abnormal bleeding, or trouble urinating. Pain lasting longer than three months is considered chronic, per MedlinePlus. Early evaluation helps find treatable causes.
Can pelvic pain be treated without surgery?
Often, yes. Treatment depends on the cause, severity, and frequency, according to MedlinePlus, and may include medication, pelvic floor therapy, nerve blocks, and neuromodulation such as sacral neuromodulation. Our page on abdominal and pelvic pain treatment options describes more, and your physician can explain which may suit you.
Is pelvic pain related to endometriosis?
It can be. Endometriosis is one possible cause of pelvic pain in women, though not the only one. Symptoms often include painful periods or pain with sex. If you suspect it, see our endometriosis pain page and speak with your physician, who can recommend appropriate evaluation.
How do I get care for pelvic pain at US Pain Care?
You can start by finding a location near you on our locations page. US Pain Care physicians evaluate chronic pelvic pain, talk through options that fit your goals, and coordinate your care. When you are ready, book your appointment online or call 1-877-940-3501 to reach your care team.
***Disclaimer:***The information provided in this article is for educational purposes only and is not intended as medical advice. It is important to consult with a qualified healthcare professional before starting any treatment program. Each individual’s medical condition is unique, and your healthcare provider can help determine the best course of action based on your specific needs and circumstances. Always seek the advice of your doctor or another qualified health provider with any questions you may have regarding a medical condition or treatment options.