

Lower Back Pain How to Treat: 5 Practical Steps and Clinical Solutions
To treat lower back pain effectively, the most reliable first steps include maintaining light physical activity, eliminating prolonged bed rest, applying strategic thermal therapy (ice followed by moist heat), performing gentle core mobility stretches, and optimizing sleep and workstation ergonomics. These practical adjustments relieve mechanical strain on irritated lumbar tissues, promote restorative circulation, and accelerate functional recovery.
The human lumbar spine consists of five robust vertebrae separated by shock-absorbing intervertebral discs and stabilized by facet joints, dense ligaments, and extensive muscular networks. Because this region shoulders the mechanical brunt of daily movements—from sitting at a desk to lifting heavy groceries—it is particularly vulnerable to strain.
Nearly 80% of adults experience lower back pain at some point in their lives, and roughly 90% of cases are classified as nonspecific mechanical back pain. This means the discomfort stems from soft tissues, minor facet irritation, or disk overload rather than severe spinal disease. Understanding understanding low back pain causes and treatments helps differentiate between nociceptive pain (dull, aching soreness arising from tissues), neuropathic pain (sharp, burning discomfort radiating into the buttocks or down the leg, known as sciatica), and nociplastic pain (centralized sensitivity). Following established clinical evaluation guidelines, identifying your primary pain phenotype is the foundational step toward picking the most effective recovery path.
Acute Lower Back Pain How to Treat at Onset
When an acute back flare strikes—whether after lifting a heavy box, an awkward twist on the pickleball court, or simply waking up stiff—the immediate bodily response is localized muscle spasm and inflammation. In the past, conventional wisdom suggested crawling into bed and staying there for days. Modern medical science demonstrates that prolonged bed rest is counterproductive. Immobility slows localized blood flow, weakens supportive spinal musculature, and prolongs stiffness.
Instead, the gold standard for acute management is relative rest paired with early mobilization. Relative rest means temporarily modifying high-impact actions, avoiding heavy lifting, and steering clear of extreme spinal flexion or rotation while maintaining light, routine daily movements. Gentle movement signals the surrounding musculature to relax and delivers vital nutrients to recovering tissues. For a detailed breakdown of early-stage protocols, exploring what are good treatments for acute lower back pain? provides actionable guidance on safe movement pacing.
Identifying Red Flag Symptoms That Require Immediate Care
While the vast majority of acute back pain episodes resolve spontaneously or with conservative at-home therapies, certain clinical indicators demand urgent or emergency medical evaluation. These warning signs, known in spine medicine as “red flags,” can indicate underlying structural emergencies such as severe nerve root compression, infection, fractures, or malignancies.
Seek immediate, same-day medical attention if your back pain is accompanied by any of the following:
- Cauda Equina Syndrome signs: New loss of bowel or bladder control (incontinence or urinary retention), or numbness in the groin, buttocks, or inner thighs (saddle anesthesia).
- Progressive neurological deficits: Sudden foot drop, progressive motor weakness in one or both legs, or rapidly worsening numbness that impairs your ability to stand or walk.
- Infection indicators: Persistent fever, chills, unexplained night sweats, or localized spinal tenderness following recent invasive procedures or systemic infections.
- Fracture risks: Severe back pain following major trauma (such as a motor vehicle accident or high fall) or minor falls in individuals with diagnosed osteoporosis.
- Oncologic concerns: Unremitting night pain that worsens when lying down, accompanied by unexplained weight loss or a prior personal history of cancer.
Adhering to rigorous clinical assessment standards ensures that serious conditions are ruled out before proceeding with at-home lifestyle adjustments.
5 Essential Lifestyle and At-Home Adjustments for Lumbar Relief
When red-flag conditions are safely excluded, managing lumbar discomfort centers on conservative spine hygiene, sensible self-management, and reducing daily mechanical stress. Implementing the following comprehensive lower back pain treatment guide strategies can dramatically accelerate tissue healing and prevent recurrent episodes.
1. Maintain Light Activity and Eliminate Bed Rest
The human spine is designed for movement. When lower back pain occurs, the natural instinct may be to lie completely flat on the couch. However, clinical evidence highlights that total bed rest leads to rapid muscle deconditioning, joint stiffness, and increased pain perception.
Engaging in active recovery—such as taking short, frequent walks on flat surfaces for 10 to 15 minutes three times a day—enhances systemic circulation, increases tissue oxygenation, and encourages the release of natural endorphins. Light aerobic activity helps wash away inflammatory byproducts pooled around irritated lumbar joints. According to official VA/DoD clinical movement guidelines, remaining physically active and gradually escalating daily walking intervals is far superior to passive rest for restoring physical function.
2. Optimize Sleep Mechanics and Thermal Therapy
We spend roughly one-third of our lives in bed, making sleep ergonomics a cornerstone of lower back recovery. Poor sleeping posture places sustained torsional stress on the lumbar spine and pelvis:
- Side Sleepers: Keep your hips and shoulders aligned by placing a firm, contoured pillow between your knees. This prevents the top leg from rotating forward, which twists the lower lumbar vertebrae and sacroiliac joints.
- Back Sleepers: Place a medium pillow beneath your knees to allow the lumbar curve to settle naturally against the mattress, reducing anterior pelvic tilt and facet joint compression.
- Stomach Sleepers: Sleeping face down forces the cervical spine into extreme rotation and exaggerates lumbar lordosis. If you must sleep on your stomach, place a thin, flat pillow under your lower abdomen and pelvis to flatten the lumbar arch.
Pair sleep adjustments with strategic thermal therapy. During the first 48 hours following an acute muscle pull, apply a cold pack wrapped in a cloth for 15 to 20 minutes every few hours to reduce localized swelling and numb sharp pain. After 48 hours, switch to moist heat therapy (such as a warm bath, moist heating pad, or hot water bottle) for 15 to 20 minutes two to three times daily. Heat increases localized microcirculation, relaxes hypertonic muscle spasms, and restores tissue elasticity.
3. Utilize Targeted Over-the-Counter Pain Relievers
Over-the-counter (OTC) medications can provide meaningful short-term comfort to help you stay mobile, but they must be used thoughtfully and according to clinical evidence.
| Medication Class | Common Examples | Primary Mechanism of Action | Clinical Back Pain Considerations | Safety & Precautionary Notes |
|---|---|---|---|---|
| Oral NSAIDs | Ibuprofen, Naproxen Sodium | Inhibits COX enzymes to reduce systemic inflammation and pain signaling | Recommended as a primary short-term oral option for acute inflammatory flare-ups | Use lowest effective dose for shortest duration; risks include GI upset/ulcers, kidney strain, and cardiovascular elevation |
| Simple Analgesics | Acetaminophen | Central pain inhibition via brain signaling pathways | Shows limited clinical superiority over placebo for acute lower back pain | Safer for those with GI ulcers; risk of liver toxicity if maximum daily limits (3,000–4,000 mg) are exceeded |
| Topical Analgesics | Lidocaine patches, Menthol/Camphor creams | Local peripheral nerve desensitization and counter-irritant sensation | Provides targeted, localized relief without significant systemic drug absorption | Ideal for focal muscular aches; do not apply over broken skin or combine directly with electric heating pads |
When using oral NSAIDs, always take them with meals. Individuals with a history of gastric ulcers, chronic kidney disease, or cardiovascular disorders should consult their physician before starting oral NSAID therapy.
4. Implement Gentle Core and Lumbar Mobility Exercises
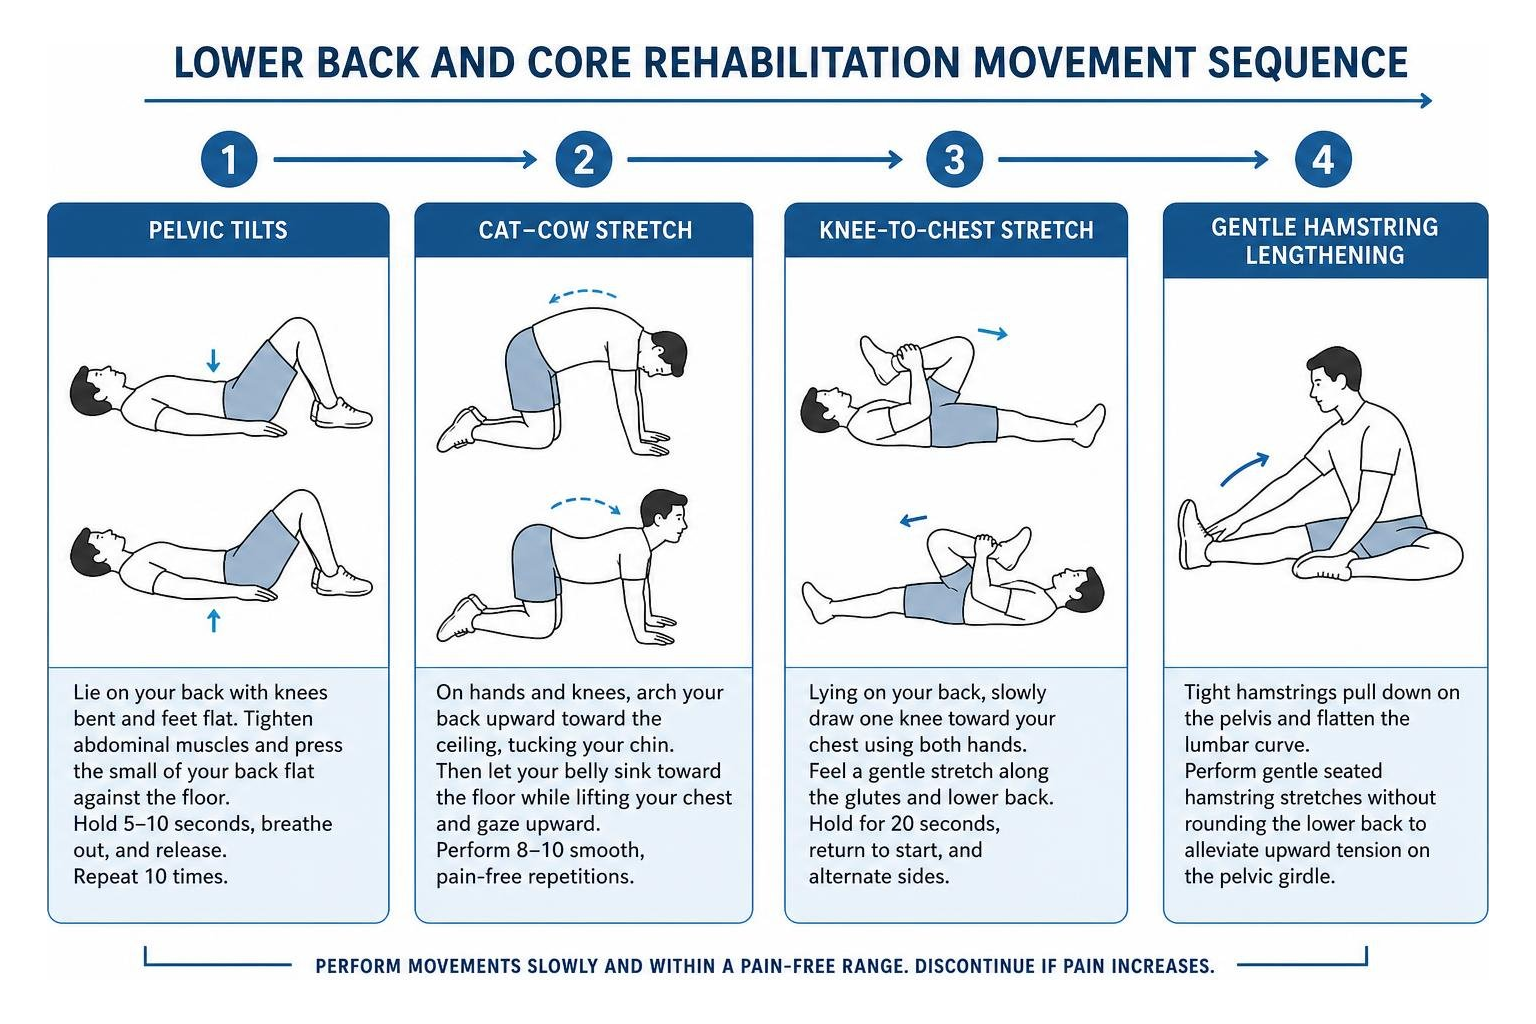
A stable core functions as an internal muscular corset that offloads mechanical forces from lumbar vertebrae and intervertebral discs. Introducing gentle, low-load mobility exercises during the recovery phase restores dynamic range of motion:
- Pelvic Tilts: Lie on your back with knees bent and feet flat on the floor. Tighten your abdominal muscles and gently press the small of your back flat against the floor. Hold for 5 to 10 seconds, breathe out, and release. Repeat 10 times.
- Cat-Cow Stretch: On hands and knees, slowly arch your back upward toward the ceiling like a stretching cat, tucking your chin toward your chest. Then slowly allow your belly to sink toward the floor while lifting your chest and gaze upward. Perform 8 to 10 smooth, pain-free repetitions.
- Knee-to-Chest Stretch: Lying on your back, slowly draw one knee toward your chest using both hands, feeling a gentle stretch along the glutes and lower back. Hold for 20 seconds, return to the start position, and alternate sides.
- Gentle Hamstring Lengthening: Tight hamstrings pull down on the pelvis, flattening the natural lumbar curve. Perform gentle seated hamstring stretches without rounding the lower back to alleviate upward tension on the pelvic girdle.
5. Correct Daily Ergonomics, Hydration, and Stress
Daily micro-habits exert a cumulative impact on spinal biomechanics. Optimizing your daily routine creates an environment where spinal tissues can thrive:
- Workstation Ergonomics: Keep computer monitors level with your eyes to prevent forward head carriage, which cascades downward into lumbar strain. Keep hips and knees bent at 90-degree angles with feet resting flat on the floor or on an ergonomic footrest. Use a small lumbar roll or contoured chair to support the inward curve of your lower back.
- Lifting Mechanics: Never bend purely at the waist to lift objects. Widen your stance, hinge at the hips, bend your knees, hold the object directly against your chest, and power the lift through your glutes and quadriceps rather than your lower back muscles. Avoid twisting your torso while carrying a load.
- Spinal Hydration: Intervertebral discs are primarily composed of water and proteoglycans. Maintaining daily fluid intake (roughly 4 to 6 cups of water daily) preserves hydrostatic pressure within the discs, ensuring effective shock absorption throughout the day.
- Smoking Cessation: Nicotine constricts microvasculature, cutting off essential oxygen and nutrient transport to avascular intervertebral discs. Smokers are up to four times more likely to develop degenerative disc disease than nonsmokers.
- Mindfulness and Stress Management: Chronic mental stress elevates systemic cortisol and creates sustained muscular guarding in the lumbar spine. People facing chronic stress or catastrophizing tend to report higher pain severity. Practicing 10 minutes of daily mindfulness-based stress reduction (MBSR), progressive muscle relaxation, or deep diaphragmatic breathing significantly lowers central nervous system pain reactivity.
Interventional and Medical Treatment Options for Severe Lumbar Pain
When symptoms do not resolve within four to six weeks of diligent conservative care, a multidisciplinary clinical approach becomes essential. Exploring advanced options through a low back pain medical treatments guide or reviewing comprehensive lumbar pain treatment options can help clarify advanced therapies.
Specialized physical therapists develop targeted active strengthening regimens that address underlying muscle imbalances, hip tightness, and core instability. Complementary modalities such as structured manual therapy, therapeutic massage, and acupuncture provide valuable adjunctive pain relief. Clinical research indicates that acupuncture can produce meaningful functional benefits when integrated into a multimodal rehabilitation plan.
Chronic Lower Back Pain How to Treat When Symptoms Persist
For chronic back pain persisting beyond 12 weeks, interventional pain physicians utilize minimally invasive, precision-targeted procedures to interrupt pain signaling pathways:
- Epidural Steroid Injections (ESIs): Administered under fluoroscopic (X-ray) guidance, ESIs deliver targeted corticosteroids and local anesthetics directly into the epidural space around compressed spinal nerves, providing rapid relief for acute radiculopathy and sciatica.
- Medial Branch Nerve Blocks & Radiofrequency Ablation (RFA): When arthritis in the lumbar facet joints causes localized pain with lumbar extension, diagnostic local anesthetic blocks are performed. If the diagnostic block yields substantial short-term relief, radiofrequency ablation uses thermal energy to deactivate the sensory medial branch nerves, blocking pain transmission for 6 to 12 months or longer.
- Spinal Cord Stimulation (SCS): For complex neuropathic pain unhelped by other measures, small electrodes implanted along the dorsal column of the spinal cord deliver mild electrical pulses that replace pain signals with soothing sensations or paresthesia-free pain relief.
Patients seeking advanced care can review the Mayo Clinic diagnostic and interventional care protocols to see how these therapies fit within a stepped clinical model.
Surgical Considerations and Decompression Procedures
Fewer than 5% of back pain patients ever require surgical intervention. Spine surgery is primarily indicated for structural nerve compression, spinal instability, or persistent functional impairment refractory to comprehensive conservative care. Clarifying what are the recommendations for treatment of lower back pain? helps ensure surgery is reserved for appropriate indications:
- Microdiscectomy: A minimally invasive procedure to remove a herniated disc fragment compressing an adjacent nerve root, rapidly relieving severe sciatica.
- Laminectomy (Decompression): The surgical removal of a small section of the vertebral bone (lamina) to widen the spinal canal and relieve pressure caused by lumbar spinal stenosis.
- Motion-Preserving Artificial Disc Replacement vs. Lumbar Fusion: In cases of severe disc collapse or structural instability (such as high-grade spondylolisthesis), surgical options include artificial disc replacement—which preserves segment mobility—or spinal fusion to stabilize painful, shifting vertebrae.
Frequently Asked Questions About Lower Back Pain Relief
How long does it usually take for lower back pain to heal?
Approximately 90% of acute lower back pain episodes resolve within 4 to 6 weeks with conservative, active self-care. However, recurrence rates range between 24% and 80% within one to two years if underlying muscular weakness, poor ergonomics, and postural habits are not addressed. When pain persists beyond 12 weeks, it is classified as chronic lower back pain and benefits from multidisciplinary medical evaluation.
Should I use heat or ice for lower back pain?
During the first 24 to 48 hours following an acute muscle strain, cold packs are generally preferred to reduce localized tissue inflammation and numb acute discomfort. After 48 hours, switch to moist heat. Heat stimulates blood flow, increases tissue elasticity, and relieves protective muscle spasms. If you suffer from chronic morning stiffness without acute swelling, heat is typically the more comforting option.
When is it time to see a spine specialist for lower back pain?
You should consult a physician or spine specialist if your back pain:
- Persists beyond 4 to 6 weeks despite consistent at-home care.
- Radiates down past your knee, causing tingling, numbness, or weakness in your leg or foot.
- Disrupts your sleep consistently throughout the night.
- Severely restricts your ability to perform routine daily activities or work duties.
Conclusion
Lower back pain can be frustrating and disruptive, but recovery is entirely achievable with the right strategy. By avoiding prolonged bed rest, prioritizing light daily movement, refining your sleep ergonomics, using medications safely, and incorporating core mobility, you take control of your spinal health.
At US Pain Care, we champion a patient-centered, whole-person approach that pairs active conservative rehabilitation with cutting-edge, minimally invasive medical therapies for patients who need deeper relief. If you are navigating an acute flare-up or seeking a structured recovery blueprint, explore our comprehensive lower back pain muscle strain treatment guide to take your next step toward lasting comfort and mobility.